Monday, October 10, 2022

Nerd Note: Statute that CMS Can't Apply Changes Retroactively

Updates 2023/03

Wolverton at AKIN law firm discusses.

https://www.mondaq.com/unitedstates/healthcare/1033896/going-retro-retroactive-rulemaking-under-the-medicare-statute-and-when-is-a-rule-really-retroactive

Section 102 of H.R.3391 - Medicare Regulatory and Contracting Reform Act of 2001

https://www.congress.gov/bill/107th-congress/house-bill/3391/text?s=1&r=33

I am not sure there is any matching regulation so 1871(e)(1) may be viewed as self implementing and may have no explicit regulatory discussing in the CMS CFR.

An example of CMS going to some detail and claiming retroactivity due to statutory instruction, under proper use of 1871 is found at:  3 FR 29699-711, Long term care hospitals, 5/22/2008.

https://www.govinfo.gov/content/pkg/FR-2008-05-22/html/08-1285.htm


From time to time a company has grounds to protest that an adverse change from CMS is being applied retroactively.  But generally, CMS's hands are tied from retroactive changes.

Here's the regulation.   

https://www.ssa.gov/OP_Home/ssact/title18/1871.htm

Rules and Policy Statements Aren't Retroactive:

(e)(1)(A) A substantive change in regulations, manual instructions, interpretative rules, statements of policy, or guidelines of general applicability under this title shall not be applied (by extrapolation or otherwise) retroactively to items and services furnished before the effective date of the change, unless the Secretary determines that—

(i) such retroactive application is necessary to comply with statutory requirements; or

(ii) failure to apply the change retroactively would be contrary to the public interest.

##

This law 1871 also contains a clause, 1871(a)(4), that a final regulation must be a "logical outgrowth" of a proposed regulation, or else it triggers a new public comment period.  For example, CMS could propose a timeline be 12 or 24 months, and finalize at 18 (a logical outgrowth).   But CMS can't propose "Policy A" and finalize as "Policy Z" when Z is wholly different policy that is not a natural outgrowth.  

##

For a Supreme Court case hinging on the details of CMS regulatory processses like the quote above, see Alina 2019:

https://www.supremecourt.gov/opinions/18pdf/17-1484_4f57.pdf

Readers might enjoy reading SSA 1871 as a whole. 

#####

From Fed reg 2008, re a retroactive rule claimed by CMS with detail:

Section 1871(e)(1)(A) of the Act provides that a substantive change 

in regulations, manual instructions, interpretative rules, statements 

of policy, or guidelines of general applicability under this title 

shall not be applied (by extrapolation or otherwise) retroactively to 

items and services furnished before the effective date of the change 

unless the Secretary determines that (i) such retroactive application 

is necessary to comply with statutory requirements; or (ii) failure to 

apply the change retroactively would be contrary to the public 

interest. As explained in the paragraph above, the MMSEA requires the 

Secretary to implement various policy changes either contemporaneously 

with the enactment of the MMSEA on December 29, 2007 or beginning with 

cost reporting periods beginning on or after December 29, 2007 as 

applicable. Therefore, under the authority of section 1871(e)(1)(A)(i) 

of


[[Page 29708]]


the Act, we are making the provisions of this interim final rule with 

comment period that implement sections 114(d) of MMSEA retroactive to 

December 29, 2007. The statute also requires that section 114(c)(1) and 

(2) be implemented beginning with cost reporting periods beginning on 

or after December 29, 2007. Therefore, under the authority of section 

1871(e)(1)(A)(i) of the Act, we are making the provisions of this 

interim final rule with comment period that implement section 114(c)(1) 

and (2) effective for cost reporting periods beginning on or after 

December 29, 2007. Additionally, as explained previously, the Secretary 

also finds that it would be contrary to the public interest if these 

provisions were not made effective on December 29, 2007 or for cost 

reporting periods beginning on or after December 29, 2007, as indicated 

above. Therefore, under the authority of section 1871(e)(1)(A)(ii) of 

the Act, we are making these changes effective under the timeframe 

noted above.

    For the same reasons noted above, we find good cause under section 

553(d)(3) of the APA to waive the 30-day delay in effective date.

tagssa

tagretroactive


Thursday, October 6, 2022

California Vetoes Bill that (Would Have) Required Biomarker Coverage

Several states, including Illinois and Louisiana, have passed bills that mandate guideline-recommended or FDA-approved biomarker coverage.   The bills vary; some are specific to cancer and some are not.

One of the most recent proposals has been vetoed by the Governor of California, after having been passed by the legislature at the end of August.

The open access news story is available at Genomeweb.

https://www.genomeweb.com/policy-legislation/california-governor-vetoes-biomarker-test-coverage-bill#.Yz76LXbMKM8

The governor's online rationale is here.

https://www.gov.ca.gov/wp-content/uploads/2022/09/SB-912-VETO.pdf?emrc=49097a


Press release from American Cancer Society here.  Univ Calif had supported the bill.

See a related study from ACS in May 2022 regarding patients' access to biomarkers and insurance coverage, here.

See the ACS Cancer Action Network home page of press releases related to access to cancer care here.

See also:  https://www.fightcancer.org/state-policy-principles-support-access-biomarker-testing and https://www.fightcancer.org/policy-resources/improving-access-biomarker-testing

Tuesday, October 4, 2022

Very Brief Blog: Two Interesting Articles in JACR

 I ran across Journal of the American College of Radiology around 2010, working on CMS PET scan policy, and I've been a fan ever since.   While lab and pathology journals (e.g. AMP's Journal of Molecular Diagnostics) have important policy articles from time to time, JACR is mostly policy and business articles, some of them really intriguing.  I've always assumed that there's crossover between imaging and lab diagnostics, both being, diagnostics.  I mused on this in March 2022 here.

Here are two interesting articles from the September issue, and if I read correctly, both are flagged as open access.

In a really unique eight-page article, Stefan Tigges MD presents diagnostic test metrics (NPV, etc) in a sophisticated way yet using a cartoon format.  Find it here.


On a wholly different topic, Brandser & Kothari talk about the pressure of unpredictable work volume and reading queues in day to day radiology, and how their group practice came up with some novel work plans to improve effectiveness.  (Some of the fastest readers in the group, were happy to get paid extra to do "bunker shifts" reading a fixed aliquot of images in queue.  And during that time - say, on a Saturday - having no other duties, and just working from home.  Sounds simple, but someone had to think of it.)  Sort of like an attorney going into the home office on Sunday and knocking out 1.5 billable hours. 

One thing I noted - while CMS doesn't have a fixed time for physician RVUs, they are often around 3 per hour.   E.g. a 45-60 minute office visit, gets 2.6 work RVUs.   This radiology practice has a standard metric of an output of 10 work-RVUs per hour.   (For an internist, that would be 4, "45 minute" office visits per hour to log 10 w-RVU per hour).  (It's like the joke about a procedure that gets on the books 37 or 42 CMS minutes, but is scheduled every 20 minutes at all clinics in the real world).   


It's a Tough World for Tests: NGS MAC LCD on Ovarian Biomarkers (Nothing Covered)

There are a number of biomarkers for detecting ovarian cancer or working up adnexal masses.

If you'd like to be prepared for a tough review picking apart your new diagnostic test, get hardened up by reading the NGS MAC article about ovarian cancer tests (A58112) and the LCD (L38371).  I just ran across these documents; they're from 2020.

My only point here, is when you enthusiastically bring your shiny new test and your one first publication in 40 patients to Medicare or another payer, you may get some pretty rough handling.  (Many startup labs don't foresee this.)

Summarizing the NGS MAC author:

  • "This is a non-coverage policy for all multi marker serum tests related to ovarian cancer testing."

Read the LCD and data review here:

https://www.cms.gov/medicare-coverage-database/view/lcd.aspx?lcdId=38371&ver=12

Read the public comment article and the NGS rebuttals, here:

https://www.cms.gov/medicare-coverage-database/view/article.aspx?articleId=58112&ver=6

##

While not the only tests reviewed, two of them, Ova1 and OVERA come from Aspira Women's Health.  Both have been FDA cleared.

https://aspirawh.com/

Nasdaq AWH

https://finance.yahoo.com/quote/AWH/financials?p=AWH


##

The same MAC has a more liberal policy for several biomarker tests, like 4KScore, which are used to guide management of an intermediate PSA like "4".  It was just updated to add EPI, MyProstateScore, and isoPSA.


The summary coverage for prostate is below.  "Coverage" decisions are obviously longer than non-coverage decisions; the latter are basically one word, "no."

Coverage Indications, Limitations, and/or Medical Necessity

One biomarker test, ordered by a physician or other qualified health care professional (i.e., NP, CNS, PA) is covered ONCE per year. For men >/ 45 years old receiving testing prior to potential biopsy, covered testing includes %fPSA, PHI, Select MDx, 4K Score or MyProstate score, in men >/ 50 covered testing additionally includes EPI and isoPSA in those men >/ 50 with a PSA > than 4ng/ml. Those men, who need a repeat biopsy in the setting of patients thought to be at higher risk despite a prior negative biopsy, covered testing includes %fPSA, PHI, 4K Score, PCA 3, Confirm Dx, MyProstate Score and isoPSA with confirmed * moderately elevated PSA (>3ng/ml and <10ng/ml; or PSA >/4ng/ml and < 10ng/ml in men > 75 years of age) with BOTH of the following... [high risk indication of cancer, or contraindication to biopsy anyway]

Brief Blog: Genomeweb Deep Dive on BCBS Requesting More Proof of NGS Validation

Interesting (subscription based) 5000 word article at Genomeweb, by Turna Ray.  She describes a major BCBS plan, Highmark, wanting additional  third-party validation on NGS tests for both somatic and germline variants.   Highmark wants this done by March 2023.   

It's not clear what the range of validating authorities is, but it's clear, right now they exclude CLIA and CAP.   (However, potentially CAP could add what they require, over time).  In the article, Highmark's Matt Fickie MD is quoted as: "CLIA and CAP are a joke, and they all know that."

Much of the article focuses on validation certified by the Center for Genomic Interpretation, led by Julie Eggington (the CGI).  (MolDx isn't mentioned, but there is a long discussion of New York State validation.)

The article is described as first of two.

  • Genomeweb article here.  (Part 2 here.)
  • One of the first links is a 2021 review on the "art and science" of variant interpretation, authors Giles to Eggington, here.
  • Find the CGI here.

###
The article quotes the familiar numbers that there are 167,000 genetic tests, that 22,000 new tests per year are marketed, etc.  But if you look at Medicare data, 90% or more of the payments are under just 10-15 codes, not leaving much room for the other 166,000 tests.  

Monday, October 3, 2022

AMA Releases Nine New Final PLA Codes (Effective Jan. 1, 2023)

Each quarter, AMA releases a new batch of PLA codes.   These were submitted about 90 days before the release date, and, will be "effective" 90 days later.   

Heads up, applications for new PLA codes are due October 4, and new regular CPT codes due November 2.  The former will be posted for comments in about a week, the latter will be posted for comments around November 14.  

Find the just-released October 1 PLA codes here:

https://www.ama-assn.org/system/files/cpt-pla-codes-long.pdf

Note that AMA issues a running tally of all PLA codes too recent to be in the current year's book.   The 2022 book went up to 0284U, and this code list funs from 0285U down to 0363U.   It also includes numerous codes with smaller or larger editorial changes in the past year.  

Quest AD Detect, 0346U, is now effective (October 1) and is being priced by CMS (at a very low price).  Myriad Genesight 0345U is also now effective October 1, and is being priced by CMS (currently at a crosswalk of $1336).   Read about the current CMS pricing on these effective-October-1 codes here.

Newly released codes for use January 1, 2023, begin at 0355U (QUEST ApoL1 risk variants.)  See full code names at the AMA PDF link above, but I'll give very short informal summaries to help orient you to the new codes.

  • 0355U, Quest APO-L
  • 0356U, Naveris, oral cancer, 17 risk score markers
  • 0357U, InterVenn, DAWN AI & Mass Spec test of 142 analytes for melanoma immuno oncology benefit
    • (See Genomeweb this week for an RNA SEQ test that may outperform PDL1 here.)
  • 0358U, FujiReBio, FDA cleared 2-biomarker CSF test for Alzheimer's
    • Note that Quest LDT plasma Alzheimer amyloid test 0346U made this summer's pricing cycle, while 0358U FujiReBio FDA CSF Alzheimer test will be in next summer's pricing cycle.
  • 0359U, Cleveland Dx, IsoPSA, PSA isoforms
  • 0360U, Biodesix Nodify CDT, 7 autoantibodies for lung cancer diagnosis
    • Biodesix frequently applies for ADLT status, so we'll watch for that on this code.
  • 0361U, Mayo NFL (neurofilament light) for neurology, digital immunoassay, quantitative
    • Next summer, we'll watch how pricing compares to Quest's 0355U.  
    • Digital assays for proteomics are a rising platform.
  • 0362U, Protean, Thyroid GuidePX, 82 genes for thyroid cancer subtypes
  • 0363U, Pacific Edge, CXBLADDER Triage, 0363U, 5 gene bladder cancer risk
    • This test was in the news over the summer.  June here.  July here.
    • Note that Pacific Edge also has codes 0012M, 0013M, the first for risk of urothelial carcinoma, the second for risk of recurrence, both are 5 gene MAAAs.  CMS Pt B use CY2020 was 1,353 for the '12M and 640 for '13M ($760).  


____


__
As I noted in a recent blog, there are some weird things in how CMS assigns hospital outpatient status indicators.  For example, 0342U (Immunovia IMMRAY Pancreatic cancer diagnostic, "E1" not payable by statute) and 0343U (MIR Scientific MIR Sentinel, prostate sncRNA test, "E1" not payable by statute).  Here.  Almost no lab codes get OPPS APC status of E1 = banned by law.   Odd.  

Tufts Policy Center Releases White Paper on Medicare & Emerging Technologies

 A major new white paper has been released by the Tufts CEVR - the Center for the Evaluation of Value and Risk in Health.   It's titled "Medicare Coverage of Emerging Technologies: Challenges and Opportunities."  Authors are Sean Tunis, Peter Neumann, James Chambers, and Nola Jenkins.

Download the paper from here:

https://cevr.tuftsmedicalcenter.org/publications/medicare-coverage-of-emerging-technologies-challenges-and-opportunities


See also a March 2022 paper by Stanford Biodesign, Ruggles et al., on the need for Medicare coverage for innovative technologies, here, here.  And CMS is updating its rules and requirements for Coverage with Evidence Developments, here and here.  I posted a five minute video update of the CMS events in mid-September, on YouTube, here with some links to sources like an AdvaMed white paper on the topic.

Back to the CEVR 33-page whitepaper released today, they highlight seven recommendations.

  1. Assess existing programs thoroughly.
  2. CMS CMS-specific processes for innovative technologies.
  3. Balance the interest of multiple stakeholders [with conflicting interests].
  4. Expand the expertise and bandwidth in CMS personnel for this topic.
  5. Clarify what "evidence for Medicare population" means.
  6. Expand the use of real world evidence.
  7. Consider a "CMS opt out option for FDA approved devices that requires limited CMS engagement."


Sunday, October 2, 2022

Very Brief Blog: Strange CMS PGX Pricing as Entertaining Video

I have joked that I thought I could use September's Medicare pricing of 7 pharmacogenetic tests as a simple teaching lesson in how the crosswalk process works for new tests.

Unfortunately, the prices half and double in unpredictable ways, and I'm unable to give a clear teaching lesson.  Maybe that is the point!  (I actually held the video for several days to see if CMS would issue an updated plan with corrections, but it didn't happen.)

I discuss the pricing of new PGX tests in both a video and a blog.

PGX VIDEO

https://www.youtube.com/watch?v=w9vfr1ZkT3M

Note this has a "humor section" the first 20 seconds. You can jump to the PGX codes at 1:37 below.

0:01 Humorous Intro and Background 1:37 The New Pharmacogenetics Codes Explained 2:39 The Odd Pricing Levels CMS Published

PGX BLOG

http://www.discoveriesinhealthpolicy.com/2022/09/the-quirky-world-of-cms.html


Friday, September 30, 2022

Very Brief Blog: Obama Speaks at Genomics Conference in San Diego

 This week, President Obama was a keynote speaker at a genomics conference in San Diego.  He spoke highly supportively of genomics and precision and medicine while criticizing our "old creaky" health system which sets up barriers to innovation.   The conference was the Illumina global users conference.  Illumina also announced new sequencing platforms (here).

I suspect President Obama was representing support for the current President Biden's reboot and refresh of Operation Moonshot for cancer.

See an open access description of the speech at Genetic Engineering News:

https://www.genengnews.com/precision-medicine/at-illumina-genomics-forum-obama-prescribes-diversity-resilience-to-drive-precision-medicine-into-practice/


Thursday, September 29, 2022

National LASKER Award Goes to Genomics: NIPT

The LASKER Award is considered one of the most prestigious in medicine, and this year it goes to the development of NIPT testing.  The awardee is Y.M. Dennis Lo MD PhD.  See article by Lo in JAMA this week:


https://jamanetwork.com/journals/jama/fullarticle/2796723


Separately, the LASKER-BLOOMBERG Public Service award goes to the creation of the "Covid 19 Dashboard."  The awardee is Lauren Gardner PhD.   Here:

https://jamanetwork.com/journals/jama/fullarticle/2796722?resultClick=1

There is also a basic science award, for the discovery of the integrins, given to Richard O. Hynes, PhD; Erkki Ruoslahti, MD, PhD; and Timothy A. Springer, PhD.  Here:

https://jamanetwork.com/journals/jama/fullarticle/2796721

86 awardees of the Lasker award have also won the Nobel price, per Wikipedia.

FDA Releases Final Guidance on Clinical Decision Support Software, Some Experts Express Shock

 On September 27, 2022, FDA releases a number of guidances for the device and software industries, including an important guidance on when "Clinical Decision Support" software crosses the line between "Non device functions" not regulated by FDA, and "Device functions" which ARE regulated by FDA.


  • See the FDA 26pp guidance here.
  • See story at Stat, including the headline:
    • "FDA says AI tools to warn of sepsis should be regulated as devices."
    • See a tweet on this by Tim Sweeney, CEO of Inflammatix.
  • See a review of several of the guidances from FDA, at PharmaPhorum here.
    • Also discusses "Pre Cert" program for software.
  • Foley-Lardner viewpoint at JD Supra here.  A longer article, also from Foley Lardner, at JD Supra here.
  • BioWorld says that leading FDA expert Brad Thompson at Epstein Becker dislikes some features of the final guidance.  See his opinion in more detail ("disaster!") at RAPS open access here.
    • Thompson remarks: “FDA clearly wants to block what Congress has done, to the point where it is reaching nonsensical conclusions about what statutory language means.”  


In overview, the guidance gives four core criteria that are the major rules applied.  These come direct from 21st Century Cures, 2016  (Sec. 3060).   In an informal summary, these are: 
  1. Software does not analyze/process a medical image or lab test pattern;
  2. The purpose is [just] displaying or analyzing medical information about the patient including clinical practice guidelines;
  3. Provides the health care professional with [just] "support or recommendations" for diagnosis and treatment;
  4. HCP independently reviews the recommendation, its basis, and does not "rely" on the software for diagnosis or treatment decisions.
Each of these rules is longer in the original FDA format and each rule gets a couple pages of discussion.   Of particular interest, Section "V" provides examples of software that is exempt, due to "non device functions," and examples of software under FDA review because the software includes "device functions."

Besides the 4 rules, and their subsequent discussion, FDA provides several pages of fictional examples of software that DOES, or DOES NOT, fit into the exemptions from review.   FDA in particular elaborates on its requirement that the HCP "reviews the recommendation" and does not "rely."

Among the examples, as in the STAT article cited above (in the context of sepsis, for example) FDA talks about how the rules could foreseeably interact with advanced alert functions embedded in EHR software like EPIC.

CDx Tests and MAAA Risk Tests

There's a rub in one of the examples of an allowed function, "recommends the HCP consider one or more legally marketed companion diagnostic tests," making LDTs a little on-edge (of course, most of us would say LDT tests are currently legally marketed, quote unquote.) Page 19.

Another highlight to think about is that many LDT MAAA tests (or polygenic risk scores, PRS tests) predict the risk for a specific disease or condition.   FDA writes that "software that provides information that a specific patient 'may exhibit signs' of a disease or identifies a...risk score for a disease or condition provides a specific preventive, diagnostic, or treatment output.  Therefore, such software would NOT satisfy Criterion 3" [= NOT be exempt from this FDA software device review.].   Page 12-13.


########

The FDA guidance lists 4 core rules, then discusses at length what they mean.  Then, the FDA provides pages of examples of software that either does, or does not, fit in the rules.   In a new book, Lorraine Daston talked about "Rules: A Short History," and this interplay between written rules, implementation, and examples (which she calls "paradigms," to describe by example.) Daston is an American historian of science based in Berlin.  She is married to noted cognitive psychologist Gerd Gigerenzer, an expert on human decision-making.
#
See a 2019 story at Fierce Healthcare, "1 in 3 misdiagnoses results in serious injury or death," here.
#
In other guidance reports, FDA seems to be happy enough with its software "Pre Cert" program, but states the program should continue under new statutory authority (report, 31pp, statutory authority, page 13.)  Here, here.

Wednesday, September 28, 2022

The Quirky World of CMS Pharmacogenetics Pricing (Fall 2022 Price Proposals)

Update.  Final pricing in late November yielded no changes except 81418, Six Gene Panel, is going to be gapfilled rather than crosswalked to $742.  

###


On Friday evening, September 23, 2022, CMS released some 100 new codes and proposed prices for CY2022, and accepts public comment for 30 days.

See my original blog here.

AMA Six-Gene Panel

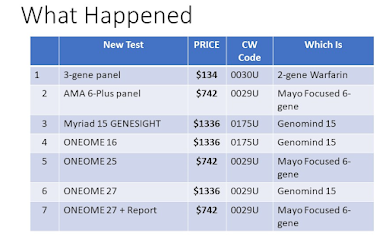
I took time to sort out the PGx codes, of which there are 7.  As I've ordered them in the cloud spreadsheet here, the first code is the AMA's own proposal for PGX of 6 or more genes, which CMS proposes to price at $742.

Myriad GeneSight

The next is the Myriad GENESIGHT test, with 15 genes, for psychiatry, which CMS proposes to price at $1336.   (The current MolDx price is $1568.64, although it used to be higher at  $2183.)

After that, the next four codes are variations of PGX panels from OneOme, and frankly, the pricing doesn't make sense to me, so maybe there's something over my head here.   Here we go.

OneOme #1

Of the four One Ome codes, I've ordered smaller to larger, with the first being the 16 gene panel.  CMS proposes to price at $1336, the same as the 15 gene Myriad panel just mentioned.  OK.

OneOme #2

The next is the OneOme 25 gene panel, and CMS drops the proposed price from $1336 to $742.  Hmm?

OneOme #3,#4

The final two OneOme codes are 0X45U/0343U, and 0X52U/0350U.   Both are 27 gene panels with identical text for the most part.   One lacks the phrase "gene drug interactions" and CMS proposes $1336.  

The other one has identical language but adds the phrase "gene drug interactions" and CMS drops the price to $742.   This is a little head-spinning for me.  I don't know if there's a typo or if there's something going on that is escaping me.

3 gene panel, RPRD

The final PGX code is a small 3 gene panel from RPRD labs in Wisconsin, CMS proposes $134, the price of a small warfarin panel 0030U.   

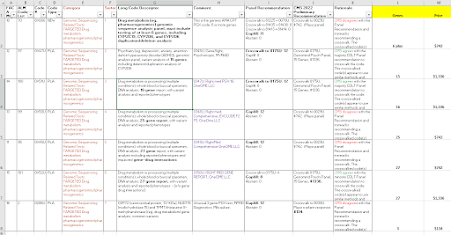
I've put a cloud spreadsheet at this link.

It's not too readable but I'm including a JPEG also:

click to enlarge

And a line chart:


Friday, September 23, 2022

CMS Releases Proposed Lab Test Prices for CY2023

After a series of summer meetings, CMS has released its proposed prices for new lab test codes, to be effective 1/1/2023.   CMS accepts public comment to October 24, and will release "final" prices in November.

Because the CMS link may update and change, I'm providing the link to the CLFS public meetings webpage, where you can scroll down to find the CY2023 proposed prices, as a Zip file holding an xls file.

https://www.cms.gov/Medicare/Medicare-Fee-for-Service-Payment/ClinicalLabFeeSched/Laboratory_Public_Meetings

About 100 Agenda Items

CMS had 105 agenda items, including a number of reconsidered (appealed) codes and including 1 code that is automatically priced as an ADLT test, the Natera minimal residual disease test.

By my tally, CMS recommends gapfill 22 times, which is about half of last year's rate.   CMS recommends a crosswalk for the other codes (90-plus), of which just two are crosswalk multiples (rather than crosswalk 1X). (*)   

CMS appears to agree 76 times and disagree 27 times with the expert panel which voted in July.  However, CMS counts an "agree" if it agrees with anybody or any subgroup on the panel.  In about 19 of those 76 agreements, CMS actually disagreed with the majority, but did agree with a minority of the panel.


A Few Notable Codes

PGX

See my follow up blog on the 7 PGX codes here.

CSF Amyloid Test

The worst surprise for me, and a red flag for anybody working in proteomics, CMS proposes to price a novel plasma-based amyloid test Beta 40/42, at only $24.   (There is an FDA authorized Fujirebio CSF test, and applied for a PLA code for it to be issued 10/2022, but this particular code is an LDT from Quest).   Panelists had all recommended gapfill for the Quest plasma amyloid code - CMS spreadsheet code 0X48U (permanent code 0346U).

An even worse policy issue for CSF amyloid tests, is that the great majority of all CSF procedures today are from hospital outpatient or inpatient environments, where CMS (to my knowledge) bundles clinical chemistry tests to the procedure cost.(**) 

For another example of pancreatic proteomic biomarker test much lower than genomic test, see "pancreatic test" section below. 

Tumor/Germline WGS = Germline WGS

A code for matching tumor/germline whole genome 0297U, is simply crosswalked to the price of the genome alone, 81425 (about $5000).

OGM: Optical genome mapping.

Two codes for optical genome mapping are both set for gapfill (0299U, 0300U). 

Castle Melanoma Test

 A majority of panelists recommended crosswalking Castle's new code 0314U to its own prior ADLT code 81529 (about $7000).  However, CMS went with a minority crosswalk to 0090U, which is only $1950.

Pancreatic Risk Tests

There are two in this cycle.  PANCRESEQ (U Pitt) 0313U, 74 genes, crosswalk to thyroid test 0026U, 112 genes.  $3600.    

In contrast, a proteomic test, Immunovia IMMRAY (Marlborough MA) PAN CAN D 0342U, about 5 biomarkers, crosswalk to 81503 (a multi marker ovarian test), only $897.   

81439: CPT Code for Low-Coverage NGS Cytogenomics

A code for low-coverage NGS for cytogenomics 81439, is set for crosswalk to 81229 (microarray).   This code is currently in the MAC gapfill process at prices that basically come very close to the 81229  price.   

The final MAC gapfill price will be published any week now, but if the November CLFS decision is crosswalk to 81229 due to the appeal, that will override the year's worth of MAC gapfill process.

Tumor Panels = Either $600 or else $3000

A range of tumor panels with PLA codes are crosswalked to either 81445 (5-50 genes) or 81455 (51+ genes), maintaining the two distant price points (one around $600, one around $3000).  See agenda 28 forward.  I wrote a white paper on CGP pricing last winter, here.

PGX

See my later blog just about this.

Quite a few PLA codes, item 8 forward, for pharmacogenomic panels.  CMS proposed to crosswalk the AMA CPT panel 8X000 for at least 6 PGX genes, to 0029U = Mayo PGX panel = $742.   

However, there are a few of the multiple PGX panels that are not crosswalked to 0029U $742, but rather  crosswalked to 0175U (Genomind) which is $1336.   This is true for 0345U (Myriad Assurex), agenda 12, 15 genes.   (Bottom line, Myriad is much better off with its own code 0345U than being coded under the generic CPT code 8X000.)  However, I believe the $1336 crosswalk is a bit lower than the current MolDx price, which in turn, is lower than the MolDx price of several years ago.

Metagenomics/Pathogens

A Hopkins-proposed code for CSF metagenomics 0323U is proposed as crosswalk to the Karius code 0152U (agenda 48).  (Typo here, CMS says it "disagrees" with the panel, but it "agrees.")

For what it's worth, my Excel with some copying and counting and highlighting is in the cloud here.

CMS Had Requested Public Comment on Crosswalking to an Unpriced Code Being Gapfilled

The context for this section is new code 0324U (#78, and 0325U #79), oncology, ovarian, spheroid cell culture, 4 drug panel.   The panelists noted on their own  that codes 324/325 are very similar to 0248U, to which it could be "crosswalked."  (They're all the same comapny, Kiyatek).   However, while 0248U is "on" the fee schedule, it has 0 national price and is currently being "gapfilled." (At $2698).     Since the company knows its two codes and two tests are nearly identical, it's in the company's interest to speed the process and just crosswalk new 0324U to slightly older code (not yet finally priced) 0248U.  

The panel also recommended that FACA Item 8, 0229U, optical genome mapping, be crosswalked to 0264U, and that FACA Item 9, 0300U be crosswalked to 0267U.   Both 264U and 267U are in the current gapfill process. 

The question of whether you can "crosswalk to a code in gapfill" is somewhat mooted because CMS proposes to crosswalk 0324U 0325U to 81535 plus 81536x3 (this is a defunct code for Helix for in vitro drug test culture, including 1 base drug and 3 add on drugs, $580 + 3x$178, $1100, a fraction of the in process gapfill of 0248U at $2698). 

click to enlarge


CMS can crosswalk new tests to the price of tests already on the CLFS.  Almost every summer, for years, someone asks if they can crosswalk to a code on the fee schedule (published by AMA) but not yet priced because it is in the gapfill process.  CMS has said no.  

Until this summer, when, CMS said provisionally that yes, you can crosswalk a new code to: a code on the fee schedule but not priced because it is in the gapfill process this summer.  

The example was a lab that had gotten a PLA code last year, which was in the midst of being favorably priced this summer.  And they wanted to crosswalk their own, even newer code, to that code in the gapfill process.  CMS said "OK" but asked for public comment.   Such a code is, in fact, "on the fee schedule" but in a very limited since, since it has no fee schedule price.

In the case at hand, it seemed reasonable for a lab to ask to be crosswalked to its own prior code being gapfilled, since the two tests were versions of one another

However, I'm equally sure that this could go wrong in several ways, if made into a general rule.  

First, CMS asks for the price of the code for which a crosswalk is requested.  This can't be provided if the target is a yet-unpriced crosswalk code.  

Second, CMS can only crosswalk to codes "on the fee schedule," but surely this meant, codes with prices on the fee schedule.  Literally, really, "on the fee schedule."  With a fee.

But third, the gapfill process code could go haywire in some cases.  

Let's say a lab gets a PLA code, and the lab doesn't show up for the summer meeting.  Therefore, CMS punts the code to gapfill, because it has no idea (except a few words of code text) what the code is.  The lab also submits no information to the MACs for gapfill (maybe the lab is not even in business any more), or, the lab does a really really bad job of providing information.  So the code is enroute to being priced very, very low.   

The issue of crosswalking to defunct or never-launched PLA codes is a real one, and applies to the crosswalk suggested by CMS for new 0324U (81535+81536x3).  I believe that test is no longer in business.

Now, you enter the picture.  And you have a brand new CPT code you've worked hard for, maybe even a Category I code.  And CMS decides to crosswalk your proud new code to the yet-uncertain, but likely horribly low, price of this gapfill code.  Ignoring all the info and arguments you're submitting, or could submit if gapfilled yourself next year.  In this situation, the lab with the new code - you - would be really upset or even face bankruptcy, but might have no recourse.  So I suggest that crosswalked to a  currently "gapfilled" and thus currently price-less code is not necessarily a good idea.


NOTES

*

CW multiples.  Agenda 24, 0229U, gets 81327x2 CW.   Agenda 102, 87428 gets CW to 78430+87400x2.   No multiple, but two codes added, for agenda 47, 0321U, 87633+87632. And agenda 51, 0X55U, 87491 + 89591.    


**
Nerd note.  The CMS hospital outpatient date of service rule applies equally to pathology tests, and clin lab tests.  However, after the DOS rule is applied, the clin lab tests are generally bundled to an event like a procedure or office visit or ER visit, while the pathology tests crosswalk into hospital outpatient "APC" prices that do pay separately, in four tiers.

***

Nerd Note.  A code could be crosswalked to a code priced on the fee schedule, but, at the same time, that target test stakeholder could be appealing to be repriced by gapfill.  So the code could be crosswalked to a code fully on the fee schedule this summer, but, switched to "no price" = gapfill, next January.  Just a hypothetical.  


McKinsey Launches 5-Part Series: The Gathering Storm, US Healthcare

On September 16, 2022, McKinsey launches the first article in a five-part series, "The Gathering Storm: Uncertain Future of US Healthcare."  The article is available both as a web version and a 7 page PDF.

https://www.mckinsey.com/industries/healthcare-systems-and-services/our-insights/the-gathering-storm-the-uncertain-future-of-us-healthcare

Turbulent factors include healthcare growth outpacing inflation and economic growth; declining productivity in healthcare (more people needed per unit of output), high administrative costs, and the need to improve efficiency (from scheduling to avoiding no shows to AI).

Find the home page for the article series, "The Gathering Storm," here:

https://www.mckinsey.com/industries/healthcare-systems-and-services/our-insights/gathering-storm

___

One page referred to a four-article series, one to a five-article series. I think the five-article count includes the home page for the series, which is itself a pretty long executive summary including a series of 2-minute videos.


Wednesday, September 21, 2022

October 12: National Academies Workshop on "Potential of Genomics across Continuum of Precision Health Care"

On October 12, 2022, National Academies of Science, Engineering, Medicine will host an all day workshop on the topic:  "Realizing the Potential of Genomics across the Continuum of Precision Health Care."


Find Streaming Site and Agenda for October 12, 2022


I am a Speaker

I am one of three speakers (from 2 pm to 3 pm) on the topic of "What logistics issues need be addressed?" for which I will discuss genomics test availability in Medicare.

####

More Context

In addition to the busy NASEM precision medicine channel here, see a March 2017 book by National Academies about Evidence Framework for Genetic Testing.  An evidence framework publication by Frueh & Quinn is among the topics discussed.

See a 2015 discussion paper posted by NAM by McCormack & Billings on defining clinical utility - here.